Neuroscientist and Parkinson’s researcher
Last updated: September 2026
A backward fall can happen quickly — while standing up, turning, reaching or stepping away from a chair. Understanding why Parkinson’s patients fall backwards can help identify the triggers and guide safer, more targeted prevention.

Falling backwards can be frightening for a person with Parkinson’s disease and for anyone supporting them. It may happen while standing still, turning, reaching upwards, stepping backwards, getting out of a chair or responding to a small loss of balance. In some cases, there is little time to react or place the hands safely before reaching the ground.
These falls are often linked to postural instability, which means the body has difficulty maintaining or recovering a stable upright position [1]. Parkinson’s can slow the automatic reactions that normally help someone regain balance. A corrective step may come too late, be too small or fail to happen at all.
However, Parkinson’s itself is not always the only explanation. Freezing, muscle stiffness, medication wearing off, dizziness when standing, reduced vision, weak muscles, unsuitable footwear and hazards around the home may also increase fall risk. A new medicine, infection or sudden change in health can sometimes make balance worse as well.
Because the causes vary, repeated backward falls should not simply be accepted as an unavoidable part of Parkinson’s. Understanding when, where and how they happen can help the healthcare team recommend more appropriate support.
This guide explains why people with Parkinson’s may fall backwards, which situations increase the risk, what practical steps may help and when professional assessment is especially important.
Why Parkinson’s can cause backward falls
Balance depends on automatic postural responses. When the body begins moving outside its stable base, the brain normally produces rapid adjustments in the trunk, legs and feet. A person may shift their weight, bend at the hips or take a quick protective step.
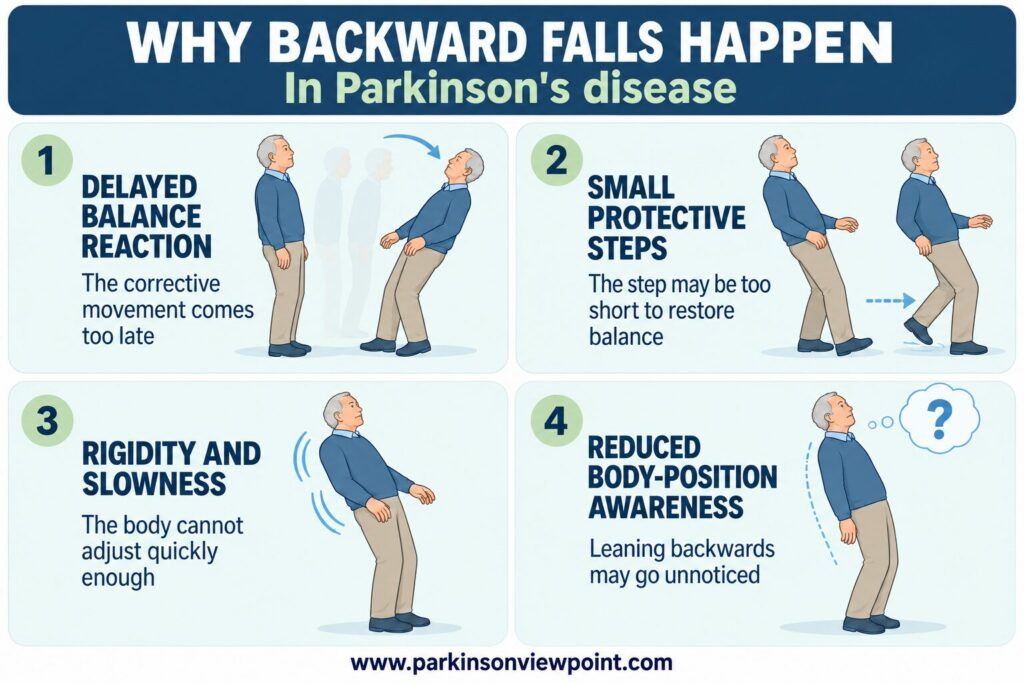
In Parkinson’s disease, these responses may become delayed, too small or otherwise ineffective [1]. If the body moves backwards, the person may take several short steps, cross their feet or fail to step at all. This backward loss of balance is sometimes described clinically as retropulsion.
Several Parkinson’s-related changes can contribute:
- Postural instability: Reduced ability to recover after being pushed or losing balance
- Bradykinesia: Corrective movements and protective steps become slow
- Rigidity: The trunk and limbs may not adjust freely
- Reduced step size: A backward step may be too short to restore stability
- Stooped or altered posture: The body’s centre of gravity and weight distribution may change
- Reduced awareness of body position: The person may not recognise how far they are leaning until balance is already lost
A clinician may assess these reactions using carefully controlled balance tests. These tests should not be attempted at home because intentionally pulling or pushing someone backwards can cause a serious fall.
Key takeaway: Backward falls can occur when the automatic step needed to restore balance is delayed, too small or absent.
Common situations that trigger backward falls
Backward falls do not always happen while walking forwards. They often occur during movements that shift body weight or require a quick change in posture.

Common triggers include:
- Stepping backwards: Moving away from a sink, cupboard, door or chair may be difficult because backward steps become short and less controlled.
- Turning: Rapid or tight turns can cause freezing, crossed feet or loss of balance.
- Standing up: Pushing backwards against a chair or failing to bring the body weight forward over the feet can lead to falling back into the seat or onto the floor.
- Reaching upwards: Looking or reaching overhead may move the centre of gravity backwards.
- Opening a heavy door: Pulling on a resistant door can unexpectedly shift the body backwards.
- Walking on slopes or uneven surfaces: Changes in the ground can demand faster balance reactions.
- Being bumped or distracted: Divided attention can make it harder to respond to a sudden change in balance.
- Medication OFF periods: Increased stiffness, slowness or freezing may raise fall risk when medication effects wear off.
- Standing after sitting or lying down: A blood-pressure drop can cause dizziness, blurred vision or faintness and should be distinguished from postural instability.
Record what happened immediately before each fall or near-fall. The trigger often provides more useful information than simply recording that a fall occurred.
Key takeaway: Identifying repeated triggers—particularly turning, stepping backwards, standing up and OFF periods—can help make prevention strategies more specific.
Other factors that can increase fall risk
Not every backward fall is caused directly by postural instability. Several treatable factors can make balance worse or reduce a person’s ability to respond safely.
These may include:
- Low blood pressure when standing
- Poor vision or an outdated glasses prescription
- Muscle weakness or reduced physical activity
- Foot pain or poorly fitting footwear
- Sedating medicines or combinations of medicines
- Urinary urgency and rushing to the bathroom
- Fatigue, dehydration or inadequate food intake
- Infection, particularly when balance worsens suddenly
- Clutter, loose rugs, poor lighting or slippery floors
- An incorrectly selected or poorly adjusted walking aid
If falls or near-falls happen after standing, read our guide to blood pressure changes and dizziness in Parkinson’s.
Tell the healthcare team if falls began after starting a new medicine or changing a dose. Parkinson’s medication may improve stiffness and slowness, but postural instability does not always respond as strongly as other movement symptoms. Medication should therefore be reviewed as one part of a broader assessment rather than treated as the only solution.
Falls that begin suddenly, increase rapidly or occur with fainting, new weakness, confusion or changes in vision require prompt medical review.
Key takeaway: A complete fall assessment should consider Parkinson’s symptoms, blood pressure, medications, vision, strength, footwear and the surrounding environment [2].
Practical ways to reduce backward falls
Fall prevention should match the person’s specific triggers, abilities and home environment. A physiotherapist or occupational therapist can assess balance reactions, walking, transfers and the need for mobility support.

Helpful strategies may include:
Practise safer standing and turning
Before standing, move towards the front of the chair, place both feet securely on the floor and bring the upper body forward. Use stable armrests if needed. After standing, pause briefly before walking.
When turning, avoid twisting quickly or pivoting on one foot. Use several controlled steps and make a wider turn. If freezing occurs, stop, reset your posture and use a cue recommended by a physiotherapist rather than forcing the next step.
Avoid unnecessary backward stepping
Whenever possible, turn around and walk forwards instead of taking several steps backwards. Be especially careful when moving away from chairs, cupboards, doors and kitchen counters.
Improve the home environment
Reduce avoidable hazards by:
- Removing loose rugs and clutter
- Keeping walking routes well lit
- Installing suitable handrails and grab bars
- Using non-slip surfaces where needed
- Keeping commonly used items within easy reach
- Choosing supportive, properly fitting footwear
For a room-by-room approach, see our guide to simple home adjustments for Parkinson’s safety.
Ask about physiotherapy
Targeted physiotherapy may include balance practice, strength training, larger-amplitude movement, stepping strategies and safe transfer techniques [3,4]. Exercises should be selected according to the person’s fall history and physical abilities.
Use mobility aids correctly
A cane or walker is helpful only when it suits the person’s walking pattern and is adjusted correctly. The wrong device—or an unfamiliar one—can sometimes increase risk. Ask a physiotherapist or occupational therapist to assess and practise its safe use.
Key takeaway: Safer movement techniques, targeted therapy, an appropriate walking aid and changes at home can work together to reduce fall risk.
When to seek professional assessment

Tell your neurologist, Parkinson’s nurse or primary-care clinician about repeated falls, near-falls or any noticeable decline in balance. Do not wait for a serious injury before asking for help.
Arrange an assessment if:
- Backward falls are becoming more frequent
- You have difficulty standing from a chair or turning safely
- Falls occur when medication appears to wear off
- You feel dizzy, faint or visually blurred when standing
- Freezing repeatedly interrupts walking
- You have started avoiding normal activities because of fear of falling
- A cane or walker no longer feels stable or suitable
- Falls began after a medication change
- Balance worsened suddenly or without a clear explanation
Frequent backward falls very early in the course of suspected Parkinson’s disease should also be discussed with a movement-disorder specialist. Although balance problems can occur in Parkinson’s, prominent early falls may occasionally suggest another neurological condition and deserve careful reassessment [5].
Seek urgent medical help after a fall if there is:
- A significant head injury
- Loss of consciousness
- New weakness, facial drooping or difficulty speaking
- Severe headache, vomiting or increasing confusion
- Inability to stand or bear weight
- Severe hip, back or neck pain
- Uncontrolled bleeding
A fall assessment may include medication review, lying and standing blood-pressure measurements, vision, muscle strength, walking, footwear, balance reactions and the home environment.
Key takeaway: Repeated or worsening falls require assessment, while head injury, loss of consciousness or sudden neurological symptoms require urgent help.
Track changes between appointments
The free Parkinson’s Daily Diary App can help you record daily gait and balance symptoms, medication status and notes about falls or near-falls.
Use the notes section to record what you were doing, where the incident happened, whether you felt dizzy or froze, and whether medication seemed to be wearing off. Bringing these patterns and your doctor-ready report to an appointment may help your healthcare team understand what has changed.
The app does not assess fall risk or replace professional evaluation. New or repeated falls should always be discussed with an appropriate healthcare professional.
Key takeaways
People with Parkinson’s may fall backwards because the automatic reactions that restore balance become delayed, too small or absent. Stiffness, slowness, freezing and reduced step size can add to the problem.
Falls may also involve treatable factors such as low blood pressure, medication effects, poor vision, muscle weakness, unsuitable footwear or hazards at home.
Record when and how falls occur. Turning, standing, stepping backwards and medication OFF periods are particularly useful patterns to identify.
Targeted physiotherapy, safer movement techniques, home adjustments and a professionally selected mobility aid may reduce risk. Repeated, worsening or early backward falls should be assessed rather than accepted as unavoidable.
Seek urgent help after a serious head injury, loss of consciousness or sudden neurological symptoms.
References
- Crouse JJ, Phillips JR, Jahanshahi M, Moustafa AA. Postural instability and falls in Parkinson’s disease. Reviews in the Neurosciences. 2016;27(5):549–555. PubMed
- Camicioli R, Morris ME, Pieruccini-Faria F, et al. Prevention of falls in Parkinson’s disease: guidelines and gaps. Movement Disorders Clinical Practice. 2023;10(10):1459–1469. Full text
- Allen NE, Canning CG, Almeida LRS, et al. Interventions for preventing falls in Parkinson’s disease. Cochrane Database of Systematic Reviews. 2022;6:CD011574. PubMed
- Osborne JA, Botkin R, Colon-Semenza C, et al. Physical therapist management of Parkinson disease: a clinical practice guideline from the American Physical Therapy Association. Physical Therapy. 2022;102(4):pzab302. Full text
- Postuma RB, Berg D, Stern M, et al. MDS clinical diagnostic criteria for Parkinson’s disease. Movement Disorders. 2015;30(12):1591–1601. PubMed